


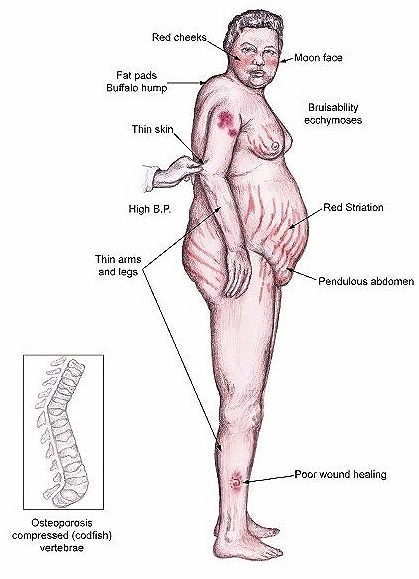
Cushing’s syndrome is a rare endocrine disorder that causes chronic cortisol excess. Although its reported incidence is about 10 cases per million people each year, the true number is likely much higher when including subclinical cases. Persistent cortisol elevation affects many systems and can result in diabetes, hypertension, high triglycerides, blood clots, osteoporosis, muscle loss, and increased cardiovascular mortality.
Recent research suggests that obstructive sleep apnea may represent another complication of Cushing’s syndrome. This relationship appears to be independent of age, gender, body mass index, and insulin resistance. Excess cortisol may weaken airway muscles, alter fat distribution around the neck, and disrupt central respiratory control, all of which increase the risk of airway obstruction during sleep.
Because both conditions share overlapping symptoms such as fatigue, weight gain, and poor sleep, one can easily mask the other. This overlap often delays recognition and treatment. Identifying sleep apnea early in patients with Cushing’s syndrome may help lower cardiometabolic risk and improve quality of life.
The reverse question also matters since patients with obstructive sleep apnea may benefit from screening for subclinical Cushing’s syndrome. For those with resistant hypertension, unexplained weight gain, or metabolic features out of proportion to body size, cortisol evaluation may reveal an underlying endocrine driver.
Recognizing this two-way connection can guide more precise diagnosis and treatment. Integrating sleep assessment into endocrine care and endocrine screening into sleep medicine can lead to better outcomes for both conditions.

References:
- Gokosmanoğlu F, Güzel A, Kilic Kan E, Atmaca H. Increased prevalence of obstructive sleep apnea in patients with Cushing’s syndrome compared with weight- and age-matched controls. Eur J Endocrinol. 2017 Mar;176(3):267-272. doi: 10.1530/EJE-16-0815. PMID: 27932409.
About Dr. Gerti Tashko, MD
Dr. Gerti Tashko, MD, is an endocrinologist in Montgomery County, Maryland. He is uniquely quadruple board-certified in endocrinology, lipidology, hypertension, and obesity medicine. His practice delivers root-cause-focused metabolic and endocrine care, available virtually and in person. He uses advanced diagnostics, personalized nutrition, and preventive medicine to improve long-term health.

EJE, Association, March 2027
Objective
Diabetes mellitus and obesity are well-known risk factors associated with obstructive sleep apnea (OSA). Cushing’s syndrome (CS) is also characterized by obesity and diabetes mellitus. However, the association between CS and OSA remains unclear. Therefore, we investigated the possible associations between CS and OSA in this study.
Patients and Methods: 30 female patients with newly diagnosed active CS and 30 age – , gender and body mass index (BMI) – matched female controls were included in this study. All of the participants were evaluated by an overnight polysomnography. OSA was defined as having anapnea-hypopnea index (AHI) score of ≥5 events/hour. BMI was recorded and iInsulin resistance was calculated by homeostasis model assessment (HOMA) scores. Fasting serum cortisol was also determined.
Results
The mean HOMA (P=0.046) and AHI (P=0.028) scores were higher in patients with cushing’s syndrome compared to the control subjects. AHI was positively correlated with the HOMA scores (r=0.281, P=0.046) in both groups.
Linear regression analysis showed that serum cortisol remained as an independent predictor for AHI after controlling for BMI and HOMA score (P<0.001).
Frequency of OSA was higher (50% vs. 23%, P=0.003) in patients with cushing’s syndrome compared to the control subjects.
Conclusions
The risk of OSA increased in patients with cushing’s syndrome compared to control subjects with similar ages and BMI levels.
Hypercortisolemia is an independent risk factor for developing OSA.
The presence of OSA needs to be considered in patients with CS.